
Shoulder replacement complication rates reach 36%. Implant survival drops to 60% over 10 to 20 years, so nearly 4 in 10 patients face implant failure in that window. A redo is harder still: the re-revision failure rate is over 23% at five years.
A total shoulder replacement is usually sold as a routine surgery. You are told it brings you back close to your younger self. That story is comfortable. It is not what the peer-reviewed data shows.
If a replacement has been booked or suggested for you, sit with the numbers below before you sign anything.
What is the failure rate of shoulder replacement?
Complication rates reach 36%. That is more than one in three patients having a complication. It is not a rare footnote in a consent form.
Over a 10 to 20 year horizon, implant survival drops to 60%. So nearly 4 in 10 patients face implant failure in that window. An implant is a machine part in a living body. Machine parts wear out.
That changes what a replacement really is. It is not a permanent cure. It is a mechanical countdown that starts the day it goes in.
What happens if a shoulder replacement fails?
Patients often think that if the implant fails, they will just get a new one. But a redo surgery is a far harder operation.
The re-revision failure rate is over 23% at five years. And the surgery itself does far more damage than the first one. Permanent bone loss and nerve injury are both real risks. Each operation removes natural anatomy that cannot be put back. Every surgeon after that has less to work with.
That is why your age at your first replacement matters so much. The clock does not reset.
The trial that should change the conversation
There is a study here that should stop you in your tracks.
In a landmark double-blind trial, labral repair surgery performed no better than a fake “sham” procedure. Patients who got the fake surgery recovered just as well as those who really went under the knife.
That does not blame surgeons. It tells us what the surgery is treating. Cutting and fixing the labrum gave the same result as a cut and nothing else. So the labral tear on the scan was likely not what caused the pain.
Does a rotator cuff tear on MRI explain my shoulder pain?
That brings us to the imaging problem.
Over 50% of pain-free people over 60 have rotator cuff tears they never knew about. They have no symptoms. They are not looking for care. The tear is just there. It is found by chance, or never found at all.
So when your MRI shows a tear and your shoulder hurts, the scan shows a link, not a cause. A finding that shows up in more than half of older adults without pain cannot explain your pain by itself.
Most of those tears are partial. Partial-thickness tears are about twice as common as full-thickness ones, and conservative care matches surgery for them. A 2024 scoping review of the treatment evidence, built on 28 level-1 trials, concluded: “The results of this scoping review do not support superiority of operative over nonoperative management” (Eubank et al., 2024). So a partial tear is treated here with guided injection, PRP into the tendon, loading of the cuff and shoulder blade, and the metabolic work, and we work to keep that shoulder out of the operating room.
You are not a “superior labral tear” on an MRI. You are a person with a shoulder worth saving. Which of those two views your doctor takes decides what gets recommended to you.
Why do rotator cuff repairs fail?
Even when a repair works on paper, the tissue often does not hold. Retear rates run 20–60%.
The reason is simple once you say it: stitches fix mechanics, not biology. A stitch holds two pieces of tissue together. It does not make a worn tendon able to heal. The biology that let the tendon fail may not have changed. If so, the repaired tissue must succeed under the same conditions that made it fail.
This is the big blind spot in assembly-line orthopedics. The structure gets fixed. The biology does not.
What is the alternative to shoulder replacement?
The other path is not doing nothing. It is treating the tissue and the setting it lives in, instead of cutting out or replacing structure.
Orthobiologic therapies — PRP, microfragmented fat tissue (MFAT), and platelet lysate — deliver your body’s own repair signals into tissue that has stopped repairing itself. On how long it lasts, this approach has shown better tendon structure and function holding past the 2- and 5-year marks.
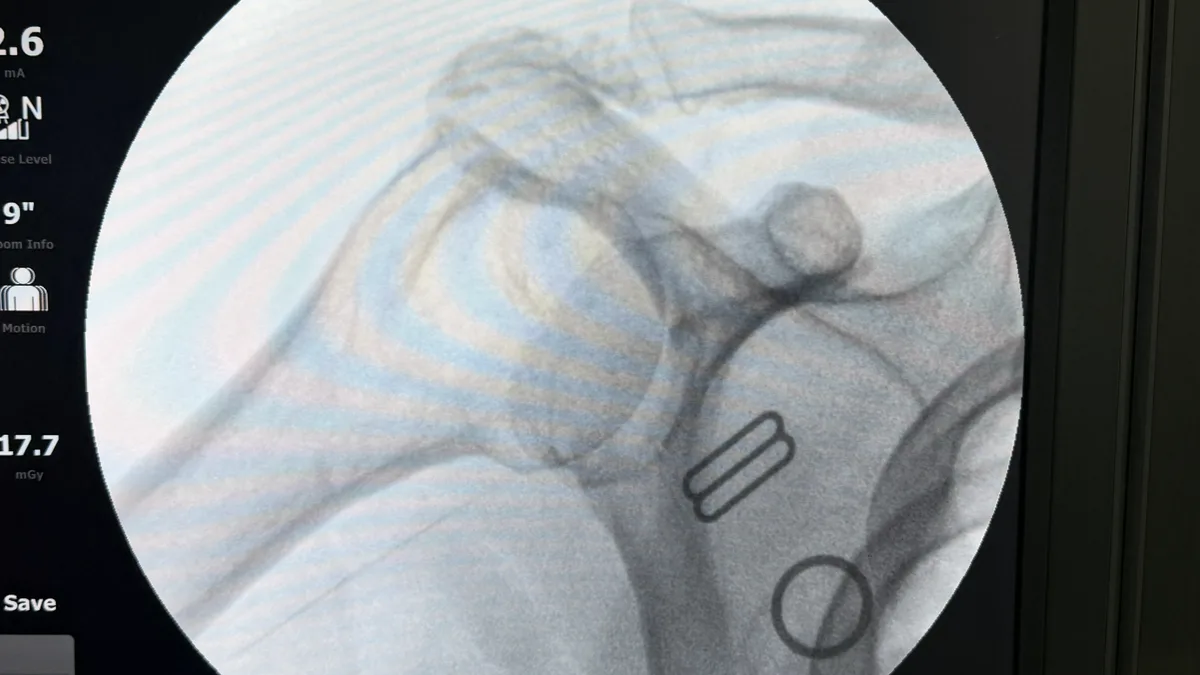
Sub-millimeter precision. Every shot is guided by ultrasound or live X-ray, never placed blind. Putting repair material into the exact damaged spot is a different treatment from putting it near the spot.
Preparing the soil. Fixing metabolic health comes first. A shot is an instruction, and a body in metabolic chaos cannot carry it out. That is why the evaluation comes before treatment, not after.
This is not cutting out structure. It is biological repair, and it keeps your natural anatomy. That matters a great deal. Natural anatomy is the one thing you cannot get back once it is removed.
Frequently asked questions
Does this mean shoulder replacement is always the wrong choice?
No. Some shoulders truly cannot be saved, and replacement is the right decision. The point here is about order and information. A surgery you cannot undo, with a 36% complication rate and 60% implant survival at 10–20 years, should be an informed choice. Make it after saving the joint has been evaluated, not by default.
For why the years before any joint replacement matter, read “Too Young for a Joint Replacement”? Don’t Waste This Window.
My MRI clearly shows a tear. Doesn’t that prove the tear is my problem?
Not on its own. More than half of pain-free people over 60 have rotator cuff tears they do not know about. Scan findings must be matched against an exam and your history. Only then can we tell if what the scan shows is really your pain source.
Partial rotator cuff tear: non-surgical and orthobiologic options, and how we approach care explains how a tear on a scan is weighed against the exam.
Should I cancel a surgery my surgeon has recommended?
Do not start, stop, or change any treatment without consulting your physician. If these questions concern you, raise them directly with your surgeon or seek a formal second evaluation before the date arrives. This page is not a directive to cancel care.
For the questions to bring to your surgeon, read Your Doctor Keeps Pushing Surgery: Questions to Ask First.
How durable are orthobiologic results for the shoulder?
The data here shows better tendon structure and function holding past the 2- and 5-year marks. Individual results vary, and not every shoulder is a candidate. That takes imaging and an exam to decide, not a website.
For the full non-surgical shoulder approach, read Shoulder Surgery Alternatives: The Biological Restoration Approach.
How long does a shoulder replacement last?
A shoulder implant is a machine part that wears out. Over a 10 to 20 year horizon, implant survival drops to 60%, so nearly 4 in 10 patients face implant failure in that window. So a replacement is less a permanent cure and more a countdown that starts the day it goes in. That is why the age of your first replacement matters.
What is the best age for a shoulder replacement?
Age matters because the implant’s clock starts on day one and never resets. Implant survival falls to 60% over 10 to 20 years. So a first replacement done earlier leaves more years for it to fail. And each redo removes natural anatomy that cannot be put back. That is why saving the joint deserves an evaluation before the first replacement, not after.
Is revision shoulder surgery harder than the first replacement?
Yes. A redo is a far harder operation, not a simple do-over. It does more damage than the first surgery. Permanent bone loss and nerve injury are real risks. The re-revision failure rate is over 23% at five years. Each operation removes natural anatomy that cannot be replaced. So every later surgeon has less to work with.
Key takeaways
- Shoulder replacement complication rates reach 36%. Implant survival drops to 60% over a 10–20 year horizon.
- A redo surgery does far more damage. The re-revision failure rate is over 23% at five years. It also risks permanent bone loss and nerve injury.
- In a landmark double-blind trial, labral repair surgery did no better than a fake (sham) procedure.
- Over 50% of pain-free people over 60 have rotator cuff tears. So a tear on your MRI is a link, not a proven cause.
- Repairs tear again 20–60% of the time. Stitches fix mechanics, while the biology underneath goes untreated.
This article is educational and is not a substitute for evaluation, diagnosis, or treatment by a physician. Individual results vary, and not every patient is a candidate for the therapies described. Do not start, stop, or change any treatment without consulting your physician.
Find out what is actually driving your pain
Regen.MD begins with a physician-led Clinical Evaluation — a review of your history, imaging, and metabolic data, and a written terrain roadmap. Evaluation is contingent upon review of your data.
Questions? Call or text us.
Sources
- Schrøder CP, Skare Ø, Reikerås O, et al. Sham surgery versus labral repair or biceps tenodesis for type II SLAP lesions of the shoulder: a three-armed randomised clinical trial. Br J Sports Med, 2017. PubMed 28495804 · doi:10.1136/bjsports-2016-097098
- Beard DJ, Rees JL, Cook JA, et al. Arthroscopic subacromial decompression for subacromial shoulder pain (CSAW): a multicentre, pragmatic, parallel group, placebo-controlled, three-group, randomised surgical trial. Lancet, 2017. PubMed 29169668 · doi:10.1016/S0140-6736(17)32457-1
- Eubank BHF, Sheps DM, Dennett L, et al. A scoping review and best evidence synthesis for treatment of partial-thickness rotator cuff tears. J Shoulder Elbow Surg, 2024. PubMed 38103720 · doi:10.1016/j.jse.2023.10.027